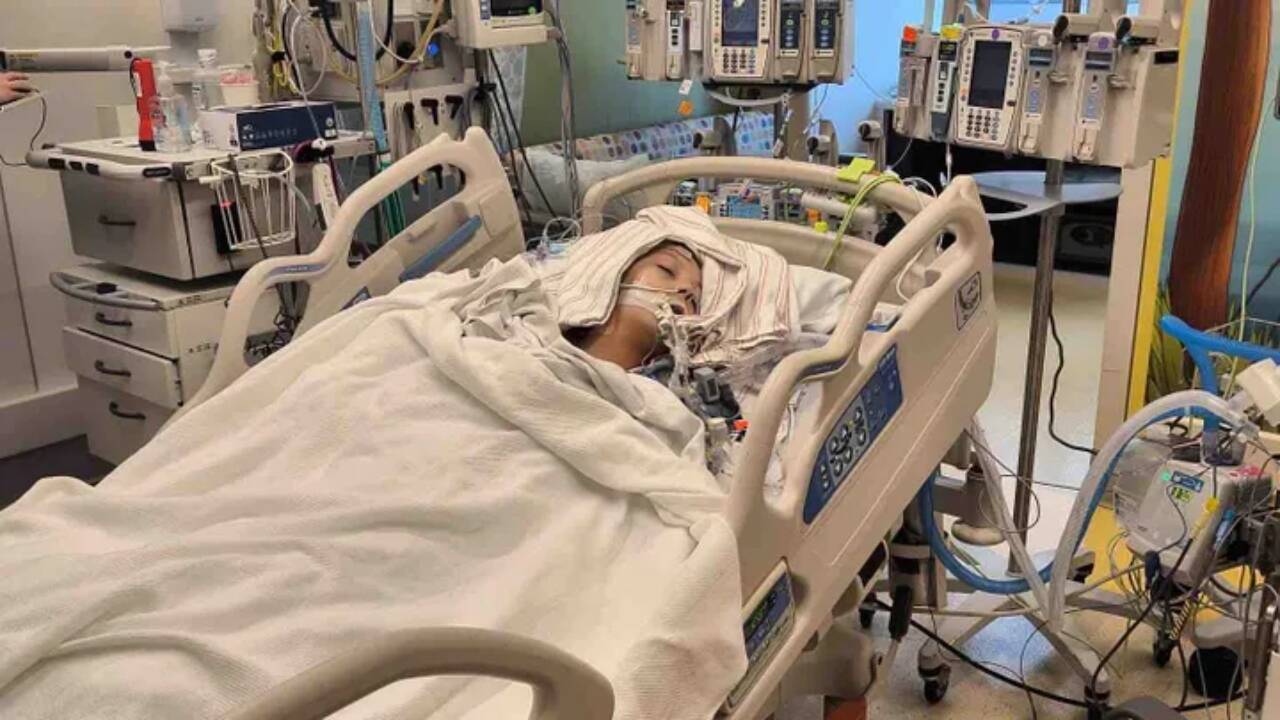
When an insurer denies a scheduled heart procedure for a child with Kawasaki disease, it doesn't just create a billing headache. It puts a ticking clock on narrowing arteries.
Stories like that of a 12-year-old boy from North Carolina—who had already undergone open-heart surgery years earlier after a Kawasaki diagnosis and still needed a stent before his coronary arteries narrowed further—show how quickly red tape collides with pediatric cardiology. When coverage gets rejected right before a procedure, families often have to choose between delaying care or traveling anyway without a clear financial safety net. You might also find this related article interesting: The Second You Push Down on Someone Else's Chest.
Here is the frustrating truth: denials like this happen far too often because insurance algorithms and rigid coverage policies are built around textbook adult heart disease, not complex pediatric vasculitis. A child with post-Kawasaki coronary damage isn't a routine adult blockage case, yet automated review criteria frequently treat them like one—or worse, flag specialized pediatric interventions as "experimental" or "not medically necessary".
How Kawasaki Disease Turns Into a Lifelong Heart Issue
Most people hear "Kawasaki disease" and picture a toddler in the hospital with a high fever, bloodshot eyes, cracked lips, and a rash. About 77% of affected children are under five, and it's the leading cause of acquired heart disease in children across developed countries. As extensively documented in detailed coverage by National Institutes of Health, the effects are notable.
Prompt intravenous immunoglobulin (IVIG) and aspirin cut the risk of severe coronary damage dramatically. Still, roughly 1 in 4 untreated children develop coronary artery problems, and even treated kids can end up with coronary artery aneurysms—bulges or weakening in the walls of the arteries that feed the heart muscle.
Years later, those damaged vessels can scar, calcify, or narrow. A kid diagnosed at age seven might reach twelve—or twenty-five—facing restricted blood flow, blood clots, or a strict choice between a catheter-based stent and repeat open-heart surgery.
- Coronary artery aneurysms: Swollen or weakened segments of coronary arteries that alter blood flow and raise clotting risks.
- Stenosis (artery narrowing): Thickened or scarred vessel walls that choke off oxygen delivery during growth spurts or exertion.
- Out-of-state specialized care: Many families travel to major pediatric heart centers because local hospitals rarely see complex post-Kawasaki reconstructions.
Why Insurers Push Back on Complex Pediatric Cardiac Care
If a pediatric cardiologist says a child needs a procedure to keep an artery open, why would an insurer push back? Honestly, it usually comes down to mismatched clinical buckets.
Standard cardiology guidelines and insurer clinical bulletins are heavily written around atherosclerotic coronary artery disease in older adults. When a 12-year-old needs catheterization, stenting, or specialized imaging for post-inflammatory coronary narrowing or aneurysm management, the case doesn't fit neat boxes. As health policy researchers have noted, patients whose cases fall outside textbook presentations often get caught in prior authorization traps.
Out-of-network referrals add another layer of friction. When a family heads out of state to a specialized pediatric center—say, traveling from North Carolina up to Boston—insurers sometimes scrutinize both the clinical necessity and the choice of facility at the exact same time.
There's also a real clinical debate among specialists themselves about the best long-term approach for complex coronary aneurysms and stenoses in younger patients, because long-term comparative trial data in children is naturally smaller than in 65-year-old adults. Insurers sometimes weaponize that nuance, labeling an individualized procedural plan as "investigational" or "experimental" even when the care team views it as urgent.
What Guidelines Actually Say About Ongoing Monitoring
The American Heart Association emphasizes that children with moderate to large persistent coronary aneurysms need ongoing cardiology care—often yearly or twice-yearly visits, imaging, and heart function tests—and eventually a structured handoff to adult congenital or Kawasaki-experienced cardiologists. Clinical updates from the American Heart Association and the American College of Cardiology also stress proactive, multidisciplinary planning for patients at high risk of major cardiac events.
In real life, though, guidelines don't automatically translate into prior authorization approval. I've seen families blindsided because a routine echo looked "okay" on paper while symptoms or narrowing trends told a different story, or because an insurer demanded documentation that took weeks to compile when the procedure was days away.
Practical Steps If a Heart Procedure Gets Denied
When a denial lands right before a scheduled procedure, waiting passively rarely works in your favor. You need a fast, parallel push on both the medical and administrative sides.
- Get the exact denial reason and clinical criteria in writing. Call the insurer immediately and ask for the specific policy bulletin, clinical guideline, or medical necessity standard used to reject the request. Don't settle for vague phone summaries.
- Ask the cardiologist for a peer-to-peer review right away. Having the pediatric cardiologist or interventional team speak directly with the insurer's medical director is often the fastest way to clear up a mismatch between adult-focused criteria and a child's anatomy.
- Request an expedited appeal if delay threatens health. Standard appeals take too long when a procedure is imminent or narrowing is progressing. Ask about urgent/expedited review timelines and document every call with dates, reference numbers, and representative names.
- File a formal written appeal with supporting records. Include the surgeon's or cardiologist's letter of medical necessity, imaging results, prior surgical history, and relevant American Heart Association guidance so the record is complete for any external review.
- Know your external escalation options. Depending on the plan type and state rules, independent external review or a complaint with your state department of insurance can challenge improper denials—though families facing immediate travel or procedure dates should talk openly with the hospital's financial counselor and care team about timing and self-pay or charity policies before making irreversible plans.



