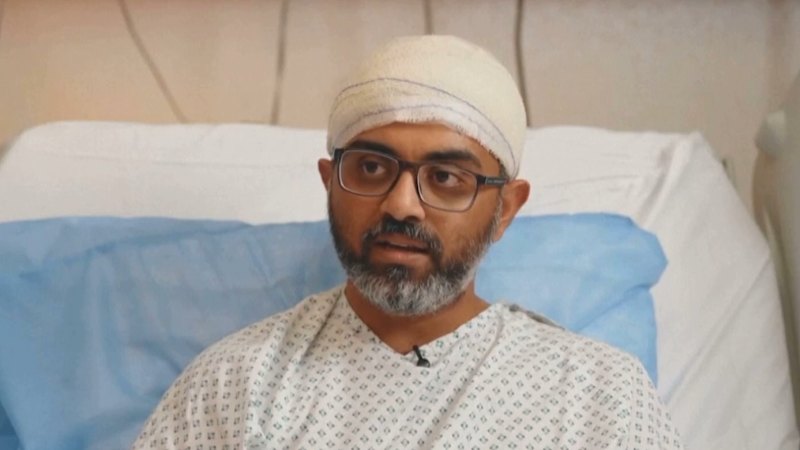
Standard media coverage of the September 30, 2026 attack aboard flydubai Flight FZ 1073 focuses on human drama: Captain Smit Machchhar speaking from a hospital bed after surviving an assault by his co-pilot, Hamam al-Hammami, before the aircraft diverted and landed safely in Tabuk, Saudi Arabia. That emotional framing captures public sympathy, yet it treats an acute operational failure as a single act of individual heroism. Treating cockpit security and emergency recovery as a story of personal grit misses the structural bottlenecks that allowed an inside threat to materialize at altitude and the exact mechanical and medical sequence that kept roughly 180 people alive.
Evaluating this event requires separating verified operational facts from active investigations and geopolitical claims. Known facts establish that a flight operating from Dubai toward Israel experienced a severe mid-air cockpit assault involving an edged or crash-axe weapon, a sharp altitude loss, an emergency diversion to Prince Sultan bin Abdulaziz International Airport in Tabuk, passenger and crew intervention, emergency hemorrhage control on board, and trauma care beginning in Saudi Arabia before transfer for further treatment. What remains under investigation includes the exact timeline of radicalization or premeditation, any external state or militant links, and the precise mechanical inputs inside the flight deck. Statements by political leaders regarding ideological indoctrination, suicide or crash intent, or foreign backing represent claims and investigative leads rather than settled legal or forensic findings.
Deconstructing Competitor Logic and Structural Blind Spots
Conventional "hero speaks from hospital" reporting relies on a simple narrative arc: sudden crisis, solitary willpower, divine or personal courage, and medical recovery. That arc is compelling for readers, but analytically incomplete. It compresses a complex multi-actor recovery into one person's bedside account and skips the causal chain linking pilot vetting, cockpit access rules, physical incapacitation, and cross-border trauma logistics.
The first analytical gap in standard coverage is treating insider threat screening as a static gate rather than a continuous system. Commercial aviation vets pilots before hiring and conducts periodic medical and proficiency checks. Once a pilot holds line authority and flight-deck privileges, the risk profile shifts from entry screening to behavioral drift, ideological capture, psychological instability, or external coercion. When an insider threat emerges from within the crew complement itself, perimeter security at the airport terminal does almost nothing to stop it.
The second blind spot is ignoring the physics and time compression of a cockpit assault. An attack inside a flight deck does not happen in a vacuum; it occurs in a confined workspace packed with flight controls, circuit breakers, radios, and emergency gear. If an assailant strikes the captain while the aircraft is cruising or maneuvering, seconds matter. A rapid pitch-down or steep descent—reports described a steep drop of thousands of feet before recovery—creates high G-loads, disorientation, and cabin panic that complicate both flying the jet and reaching the flight deck.
The third omission is underestimating cross-border diversion and trauma friction. Landing an injured captain in a neighboring country creates immediate operational and medical handoffs. Emergency surgical stabilization in Saudi Arabia followed by onward medical transfer tests diplomatic clearances, hospital trauma capacity, language and clinical handover accuracy, and insurance or sovereign coverage pathways. Focusing solely on a bedside video call hides the logistics that turn a survivable landing into a full survival outcome.
The Four Pillars of Flight-Deck Resilience
To analyze any cockpit security breach rigorously, look at four interdependent pillars: Continuous Vetting, Physical & Procedural Containment, In-Flight Recovery & Cabin Integration, and Diversion & Trauma Continuity. Weakness in one pillar multiplies the load on the others.
Continuous Vetting and Insider Risk Detection
Aviation safety has long relied on Crew Resource Management—the training system that teaches flight crews to challenge errors, cross-check actions, and share workload—to catch human mistakes. CRM works well for fatigue, task saturation, or misread instruments. It is far less effective against covert hostile intent disguised as normal line flying.
Continuous insider risk management depends on three operational mechanisms:
- Behavioral and life-event monitoring: Tracking unexplained shifts in personal conduct, extreme ideological rigidity, financial stress, or withdrawal from peers without turning routine reporting into a punitive trap that drives pilots into secrecy.
- Two-person occupancy and access discipline: Ensuring no single crew member has unchallenged, prolonged control over critical flight-deck systems during vulnerable phases of flight, while balancing anti-hijacking door locks against insider lockouts.
- Cross-agency intelligence sharing: Connecting airline security and civil aviation authorities with national security databases so warning signs outside the airline—such as extremist contacts or travel anomalies—reach flight-operations risk managers before a flight departs.
A major operational tension exists here. Overly aggressive surveillance or hair-trigger grounding harms morale and may push troubled crew members to hide symptoms. Conversely, treating psychological and ideological screening as a box-ticking exercise leaves blind spots that only surface during a crisis.
Physical Containment Inside a Confined Workspace
Post-9/11 cockpit doors were engineered primarily to keep external attackers out of the flight deck. That design assumes the threat is outside the door. When the threat is already seated on the right or left seat, hardened doors can even delay outside rescue if entry codes, override logic, or physical barriers slow cabin crew and passengers from intervening.
Inside the cockpit, space constraints shape every physical action. Crash axes and fire extinguishers are mounted for emergency access, not hand-to-hand combat, yet in a close-quarters struggle any heavy or sharp tool becomes a force multiplier. When a pilot suffers head, limb, or torso trauma—including severe bleeding or skull injury—fine motor control degrades fast. Opening a door, disengaging or re-engaging autopilot and thrust, and communicating on radio frequencies all compete for failing physical capacity.
In-Flight Recovery and Cabin Integration
A flight-deck assault only ends when the aircraft is stabilized, the threat is neutralized, and a qualified crew member is flying the airplane to a safe runway. In Flight FZ 1073's recovery, accounts point to a chain reaction: the wounded captain fought to reach and open the cockpit door, cabin crew and passengers—including passengers with medical training—moved into the breach to help restrain or respond and stop life-threatening bleeding, and the crew diverted to Tabuk.
Consider how cabin intervention changes the survival equation. Flight attendants train for unruly passengers and cabin emergencies, not mid-air cockpit combat. When passengers with clinical skills, such as a dentist or physician on board, assist with hemorrhage control on a cabin or flight-deck floor, they bridge the gap between point-of-injury trauma and hospital care. Still, passenger intervention carries real risks: untrained bystanders can get injured, crowd narrow aisles, or interfere with crew containment procedures if commands are not clear and unified.
Diversion and Cross-Border Trauma Continuity
Diverting an international flight to an alternate airport—especially across regional borders—turns an aviation incident into a multi-agency logistics operation. Air traffic control must clear an urgent descent and approach; airport rescue and firefighting must stage for potential medical or security contingencies; ground security must secure the aircraft and detain or interview suspects; and local hospitals must receive trauma patients immediately upon arrival.
For a pilot with severe head and extremity injuries, the first hour after touchdown determines neurological and vascular outcomes. Rapid stabilization and neurosurgical care in the diversion country buy critical time before specialized transfer. Yet cross-border care also introduces friction: transferring medical imaging and surgical notes, coordinating family access, managing consular notifications, and resolving billing or sovereign coverage across jurisdictions all require pre-established playbooks rather than ad-hoc improvisation.
The Cost Function of Cockpit Security and Crisis Response
Every aviation security measure carries an operational cost function. Airlines and regulators do not optimize for zero risk in isolation—zero risk is impossible in complex socio-technical systems—but for acceptable risk per flight hour subject to economic, regulatory, and human constraints.
The primary variables in this cost function include:
- Direct screening and compliance costs: Expanded background checks, psychological evaluations, data integration, and administrative overhead passed onto carriers and regulators.
- Operational friction and delay costs: Longer turnaround times, crew scheduling buffers, reroutings, and diversion penalties when security protocols trigger alerts or alternate landings.
- Human capital and trust costs: Potential friction between management and pilot unions if monitoring feels intrusive, balanced against crew confidence that the employer protects them from insider harm.
- Tail-risk catastrophe costs: The catastrophic human, reputational, financial, and geopolitical fallout of an uncontained cockpit takeover or hull loss.
A simple conceptual example illustrates the trade-off. Suppose an airline adds an extra layer of continuous psychological and security review plus stricter flight-deck access rules. Per-flight costs rise slightly through compliance and occasional scheduling friction. If that extra layer prevents even one catastrophic loss-of-control event over a decade, the avoided hull, liability, and brand damage dwarfs the routine screening outlay. Conversely, if new rules are vague or poorly calibrated—requiring paperwork without clear threat indicators—they raise airline burden without reliably catching a determined insider.
Step-by-Step Operational Playbook for Post-Incident Review
Airlines, regulators, and airport operators analyzing a cockpit insider attack should execute a disciplined review sequence rather than relying on initial media narratives.
- Reconstruct the timeline from objective flight and cabin data. Align flight data recorder parameters, air traffic control audio, cabin interphone logs, and witness accounts to map exact timestamps for the initial threat, altitude excursion, door opening, threat containment, diversion decision, and touchdown.
- Audit pre-incident vetting and reporting pathways. Examine every touchpoint where behavioral, medical, or security signals could have appeared—training records, line checks, medical exams, peer reports, and external security clearances—to identify where information stalled or went unanalyzed.
- Stress-test flight-deck door and intervention protocols. Evaluate how cockpit locking logic, crew alert signals, and cabin-to-cockpit entry procedures performed when the threat originated inside the flight deck rather than outside.
- Review emergency medical and cabin-crew readiness. Assess first-aid kit contents for severe hemorrhage control, cabin crew training for violent cockpit or cabin events, and how spontaneous medical help from passengers was coordinated safely.
- Verify cross-border diversion and repatriation workflows. Check how quickly medical records, surgical updates, family support, consular teams, and replacement aircraft arrangements moved across borders after landing in Tabuk.
- Publish clear, enforceable standards without ambiguity. Convert lessons learned into concrete procedures with defined thresholds and responsibilities, avoiding vague directives that strain operations without closing security gaps.
Limitations and Unresolved Risks
Even the strongest aviation safety framework has hard boundaries. First, no screening protocol can predict every human turn toward violence or extremism with certainty. Individuals can mask intent until moments before acting, and investigations into complex cases often take months to establish full motive and networks.
Second, physical cockpit defenses involve competing hazards. Making flight-deck entry harder protects against external hijackers, while making entry easier speeds rescue during an internal assault. Engineering and procedures must manage that trade-off rather than pretending it disappears.
Third, post-trauma recovery extends far beyond hospital discharge. Surviving a violent cockpit struggle and steep descent leaves lasting physical, cognitive, and psychological effects on injured pilots, surviving crew members, and passengers. Medical clearance to fly or work again requires rigorous, compassionate clinical evaluation rather than public momentum or political praise.
Strategic Play
Civil aviation regulators and airline operators should pair continuous, intelligence-linked insider risk screening with standardized emergency cockpit-breach and hemorrhage-control drills across flight and cabin crews. Rather than treating the survival of Flight FZ 1073 as proof that individual courage alone is an adequate backstop, carriers and aviation authorities should codify the exact sequence that saved lives—rapid threat containment, immediate bleeding control, disciplined diversion to the nearest suitable airfield, and seamless cross-border trauma handover—into mandatory operational playbooks before the next edge case occurs.



